
1 · SNAPSHOT
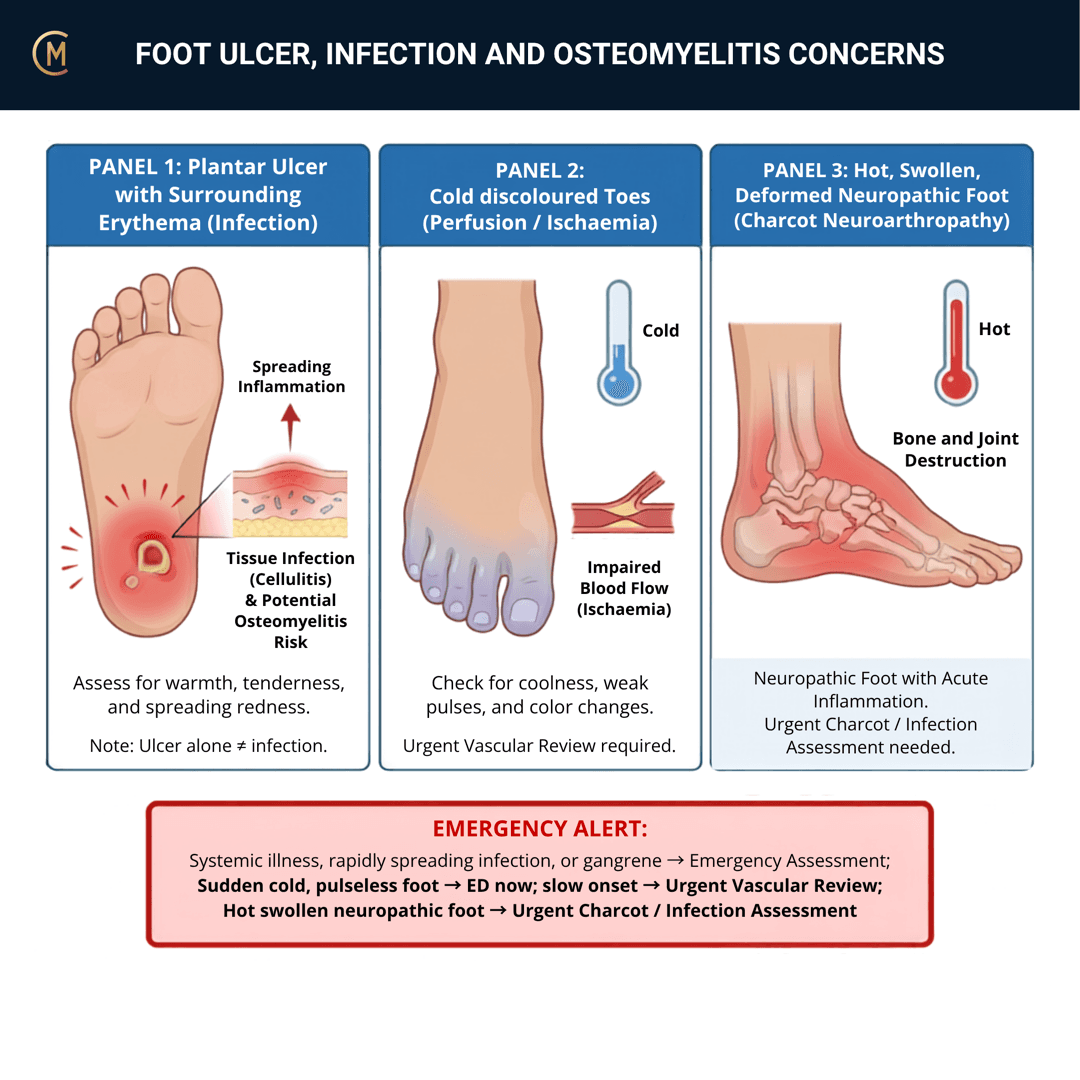
This entire page is free, permanently — all seven sections. Red flag content is never gated in CliniStudy.
Who: Diabetes. Neuropathy. Immunocompromise. Peripheral artery disease. Recent foot surgery. Any open wound on any of the above.
What: Soft tissue infection, deep infection, osteomyelitis, or an infected ulcer — often more than one at once.
How it behaves: Persistent or spreading pain, swelling, redness and warmth. Sometimes discharge or necrotic tissue. And sometimes far less pain than the tissue damage deserves.
The one thing to take from this page:
Absence of severe pain is the trap, not the reassurance. Neuropathy removes the alarm that would normally bring this patient in early.
| Australian guideline exists | Yes — Commons et al. 2022, part of the 2021 Australian diabetes-related foot disease guidelines |
| Its position | In diabetes-related foot disease, all infections are serious. Urgent referral when spreading, deep, systemic, ischaemic or ulcer-associated |
| Your role | Recognise · protect · offload · escalate · do not load through it |
✅ This is one of the few red flag patterns in CliniStudy with a real Australian anchor [1]. It covers diabetes-related foot infection. It does not cover non-diabetic or post-surgical infection, and it is not written for physiotherapists — the escalation principle transfers, the grading and antibiotics do not.
2 · SE — THE SUBJECTIVE PATTERN (the 70%)
Five stages, in your course's order. The risk history does most of the work here — because the symptom that would normally dominate may be missing.
MAIN PROBLEM
"My foot's swollen and it's gone red up the top."
"There's a sore that isn't healing."
"It's not really sore, but it looks angry."
That last sentence is the one to worry about.
BODY CHART
- Mark the erythema border and date it. A spreading margin is measurable evidence and the receiving clinician will want it.
- Draw any wound, ulcer or breach — location, size, and whether there is discharge.
- Map sensation as an area, not a point. Where does protective sensation stop?
BEHAVIOUR
- Ask about swelling through the day and whether elevation changes it.
- Ask what happens on walking — and remember that a neuropathic foot may report very little.
- Do not use pain as your severity gauge on this pattern. It is the one presentation where it fails you.
HISTORY
- Diabetes — how long, how well controlled, and who manages it.
- Known neuropathy, known peripheral artery disease, previous ulcer, previous amputation. Previous ulceration is the strongest predictor of the next one.
- Recent foot surgery, procedure or injury — including a trivial one. A blister, a burn, a nail.
- Immunosuppression — medication, treatment, or a condition their doctor manages.
- How long has the wound been there, and is it getting bigger?
SPECIAL / SCREENING QUESTIONS
- Fever, chills, rigors, feeling generally unwell. Systemic features escalate this to an emergency (Balakrishnan et al. 2025).
- Recent change in glycaemic control — patients often notice their numbers went strange before they noticed the foot.
- Claudication, rest pain, cold foot, non-healing wounds elsewhere — the peripheral artery disease screen (Fitridge et al. 2024).
Assessing this region? Download the Ankle & Foot assessment template →
3 · HYPOTHESIS RANKING
| Competing pattern | The one discriminating feature |
|---|---|
| Neuropathic ulcer without infection | A painless ulcer with intact surrounding tissue, no warmth, no spreading erythema, no systemic features. Still needs offloading and wound care — it just isn't an emergency today. |
| Charcot neuroarthropathy | A hot, swollen, neuropathic foot without an ulcer and without systemic illness. Still urgent — different pathway, same-day referral, and the foot is protected either way. No single sign separates it from infection — the call takes history, exam, imaging and labs together (Rogero et al. 2024) [21]. |
| Cellulitis | Spreading erythema and warmth without deep bone involvement. Treat as osteomyelitis until it is excluded — the distinction is made with imaging and labs, not by looking. |
Note what the ranking does here. It does not change today's action for any of the three. Offload, protect, refer. What it changes is what you say in the referral, and how urgently the phone gets picked up.
4 · RED FLAGS — DON'T MISS THIS
This section is free, on every pattern, forever. Safety is never gated.
The escalation set
| Finding | What it means | What you do |
|---|---|---|
| Fever, rigors, tachycardia, systemically unwell | Possible diabetic foot attack / sepsis | 🚑 Emergency department now |
| Rapidly spreading erythema, crepitus, necrosis, foul discharge | Deep or severe infection | 🚑 Emergency department now |
| Hot, red, swollen foot ± ulcer in diabetes | All infections in this group are serious | Same-day medical review |
| Ulcer probing deep, exposed bone, ulcer over a bony prominence | Osteomyelitis suspected | Same-day medical review |
| Sudden cold, pale, pulseless or painful foot | Acute limb ischaemia — prognosis is severe, and the longest delay is before the patient sees any doctor [22] | 🚑 Emergency department now |
| Rest pain, a non-healing wound, a foot that has been cold or pale for a while | Peripheral artery disease | Same-day vascular assessment |
| Hot swollen neuropathic foot, no ulcer, no fever | Possible Charcot | Same-day review, protect and offload |
The three rules that survive everything else
1. Absence of severe pain clears nothing. It is the commonest reason this presentation arrives late.
2. A normal X-ray clears nothing. Early radiographs miss osteomyelitis; equivocal and high-risk cases go to MRI or nuclear imaging.
3. Do not load or treat through it. No mobilisation, no needling, no manual therapy, no progressive loading through infected or ulcerated tissue at any severity.
Cross-links: Lateral ankle sprain · Plantar fasciopathy · Infection / malignancy
5 · OE — THE OBJECTIVE (the 30%)
Members
Sections 5 to 7 are for members
The objective exam, management and pearls, plus the six-minute lesson and the debrief. Free with an account.
Sign in or join free6 · MX — MANAGEMENT ESSENTIALS
Members
Sections 5 to 7 are for members
The objective exam, management and pearls, plus the six-minute lesson and the debrief. Free with an account.
Sign in or join free7 · CLINICAL PEARLS + RETRIEVAL CHECK
Members
Sections 5 to 7 are for members
The objective exam, management and pearls, plus the six-minute lesson and the debrief. Free with an account.
Sign in or join freeMembers
The 5-minute lesson is for members
Twelve slides on this pattern: what you'll hear, what to examine, what to do. Free with an account.
Sign in or join freeGuideline anchor
Australian guideline on the management of diabetes-related foot infection (Commons et al. 2022, PMID 35676695), part of the 2021 Australian evidence-based guidelines for diabetes-related foot disease.
More
This is one of the few red flag patterns in CliniStudy with a genuine Australian anchor. Supplemented internationally by the IWGDF/IDSA infection guideline (Senneville et al. 2024, PMID 37779323), the IWGDF offloading guideline (Bus et al. 2024, PMID 37226568) and the intersocietal IWGDF/ESVS/SVS peripheral artery disease guideline (Fitridge et al. 2024, PMID 37726988) — the last two co-authored by Australian researchers.
The Australian guideline covers diabetes-related foot infection specifically. It does not cover non-diabetic foot infection, post-surgical infection, or the immunocompromised patient without diabetes, and it is not written for physiotherapists. The escalation principle transfers; the specific severity grading and antibiotic content is medical.
Members
The evidence summary is for members
Verified diagnostic accuracy, where the evidence stands and what it doesn't settle. Free with an account.
Sign in or join freeSources · 20
ShowHide
Every source on this page resolves and title-verifies against PubMed. Newest first.
- 2022Commons et al. (2022). Australian guideline on management of diabetes-related foot infection: part of the 2021 Australian evidence-based guidelines for diabetes-related foot disease. Journal of foot and ankle research, 15(1), 47. https://doi.org/10.1186/s13047-022-00545-4
- 2007Lavery et al. (2007). Probe-to-bone test for diagnosing diabetic foot osteomyelitis: reliable or relic?. Diabetes care, 30(2), 270-4. https://doi.org/10.2337/dc06-1572
- 2014Markanday (2014). Diagnosing diabetic foot osteomyelitis: narrative review and a suggested 2-step score-based diagnostic pathway for clinicians. Open forum infectious diseases, 1(2), ofu060. https://doi.org/10.1093/ofid/ofu060
- 2016Hingorani et al. (2016). The management of diabetic foot: A clinical practice guideline by the Society for Vascular Surgery in collaboration with the American Podiatric Medical Association and the Society for Vascular Medicine. Journal of vascular surgery, 63(2 Suppl), 3S-21S. https://doi.org/10.1016/j.jvs.2015.10.003
- 2017Giurato et al. (2017). Osteomyelitis in diabetic foot: A comprehensive overview. World journal of diabetes, 8(4), 135-142. https://doi.org/10.4239/wjd.v8.i4.135
- 2020Lipsky et al. (2020). Guidelines on the diagnosis and treatment of foot infection in persons with diabetes (IWGDF 2019 update). Diabetes/metabolism research and reviews, 36 Suppl 1, e3280. https://doi.org/10.1002/dmrr.3280
- 2020Llewellyn et al. (2020). Imaging for detection of osteomyelitis in people with diabetic foot ulcers: A systematic review and meta-analysis. European journal of radiology, 131, 109215. https://doi.org/10.1016/j.ejrad.2020.109215
- 2021Lipsky & Uçkay İ (2021). Treating Diabetic Foot Osteomyelitis: A Practical State-of-the-Art Update. Medicina (Kaunas, Lithuania), 57(4). https://doi.org/10.3390/medicina57040339
- 2022Truong et al. (2022). Meta-Analysis: Outcomes of Surgical and Medical Management of Diabetic Foot Osteomyelitis. Open forum infectious diseases, 9(9), ofac407. https://doi.org/10.1093/ofid/ofac407
- 2022Wang et al. (2022). Diabetic foot ulcers: Classification, risk factors and management. World journal of diabetes, 13(12), 1049-1065. https://doi.org/10.4239/wjd.v13.i12.1049
- 2023Haghverdian et al. (2023). Clinical Pathway for the Management of Diabetic Foot Infections in the Emergency Department. Foot & ankle orthopaedics, 8(1), 24730114221148166. https://doi.org/10.1177/24730114221148166
- 2023Cortes-Penfield et al. (2023). Evaluation and Management of Diabetes-related Foot Infections. Clinical infectious diseases : an official publication of the Infectious Diseases Society of America, 77(3), e1-e13. https://doi.org/10.1093/cid/ciad255
- 2023Calvo-Wright et al. (2023). Is the Combination of Plain X-ray and Probe-to-Bone Test Useful for Diagnosing Diabetic Foot Osteomyelitis? A Systematic Review and Meta-Analysis. Journal of clinical medicine, 12(16). https://doi.org/10.3390/jcm12165369
- 2023Woo et al. (2023). State-of-the-art update for diagnosing diabetic foot osteomyelitis: a narrative review. Journal of Yeungnam medical science, 40(4), 321-327. https://doi.org/10.12701/jyms.2023.00976
- 2024Bus et al. (2024). Guidelines on offloading foot ulcers in persons with diabetes (IWGDF 2023 update). Diabetes/metabolism research and reviews, 40(3), e3647. https://doi.org/10.1002/dmrr.3647
- 2024Fitridge et al. (2024). The intersocietal IWGDF, ESVS, SVS guidelines on peripheral artery disease in people with diabetes and a foot ulcer. Diabetes/metabolism research and reviews, 40(3), e3686. https://doi.org/10.1002/dmrr.3686
- 2024Senneville et al. (2024). IWGDF/IDSA guidelines on the diagnosis and treatment of diabetes-related foot infections (IWGDF/IDSA 2023). Diabetes/metabolism research and reviews, 40(3), e3687. https://doi.org/10.1002/dmrr.3687
- 2024Lauri et al. (2024). Diagnostic imaging of the diabetic foot: an EANM evidence-based guidance. European journal of nuclear medicine and molecular imaging, 51(8), 2229-2246. https://doi.org/10.1007/s00259-024-06693-y
- 2025Balakrishnan et al. (2025). Diabetic foot attack: Managing severe sepsis in the diabetic patient. World journal of critical care medicine, 14(1), 98419. https://doi.org/10.5492/wjccm.v14.i1.98419
- 2025Parveen et al. (2025). Comprehensive review on diabetic foot ulcers and neuropathy: Treatment, prevention and management. World journal of diabetes, 16(3), 100329. https://doi.org/10.4239/wjd.v16.i3.100329
Generic measures that also apply
- Borg RPE
Borg Rating of Perceived Exertion Scale (6-20)
perceived exertion · 1 items · 1 min
- GROC
Global Rating of Change Scale
perceived change since baseline · 1 items · 1 min
- NPRS
Numeric Pain Rating Scale
pain intensity · 1 items · 1 min
- PGIC
Patient Global Impression of Change
perceived change since baseline · 1 items · 1 min
- PSFS
Patient-Specific Functional Scale
patient-generated function · 3 items · 2 min
- SANE
Single Assessment Numeric Evaluation
patient-rated function as a percentage of normal · 1 items · 1 min
- VAS
Visual Analogue Scale
pain intensity · 1 items · 1 min
- Borg CR10
Borg Category Ratio 10 Scale
perceived exertion or symptom intensity, ratio scale · 1 items · 1 min
- GAS
Goal Attainment Scaling
individualised goal achievement · 10 min
Did this page do its job?
CliniStudy is in beta. One tap is enough — it decides what gets fixed first.