
1 · SNAPSHOT
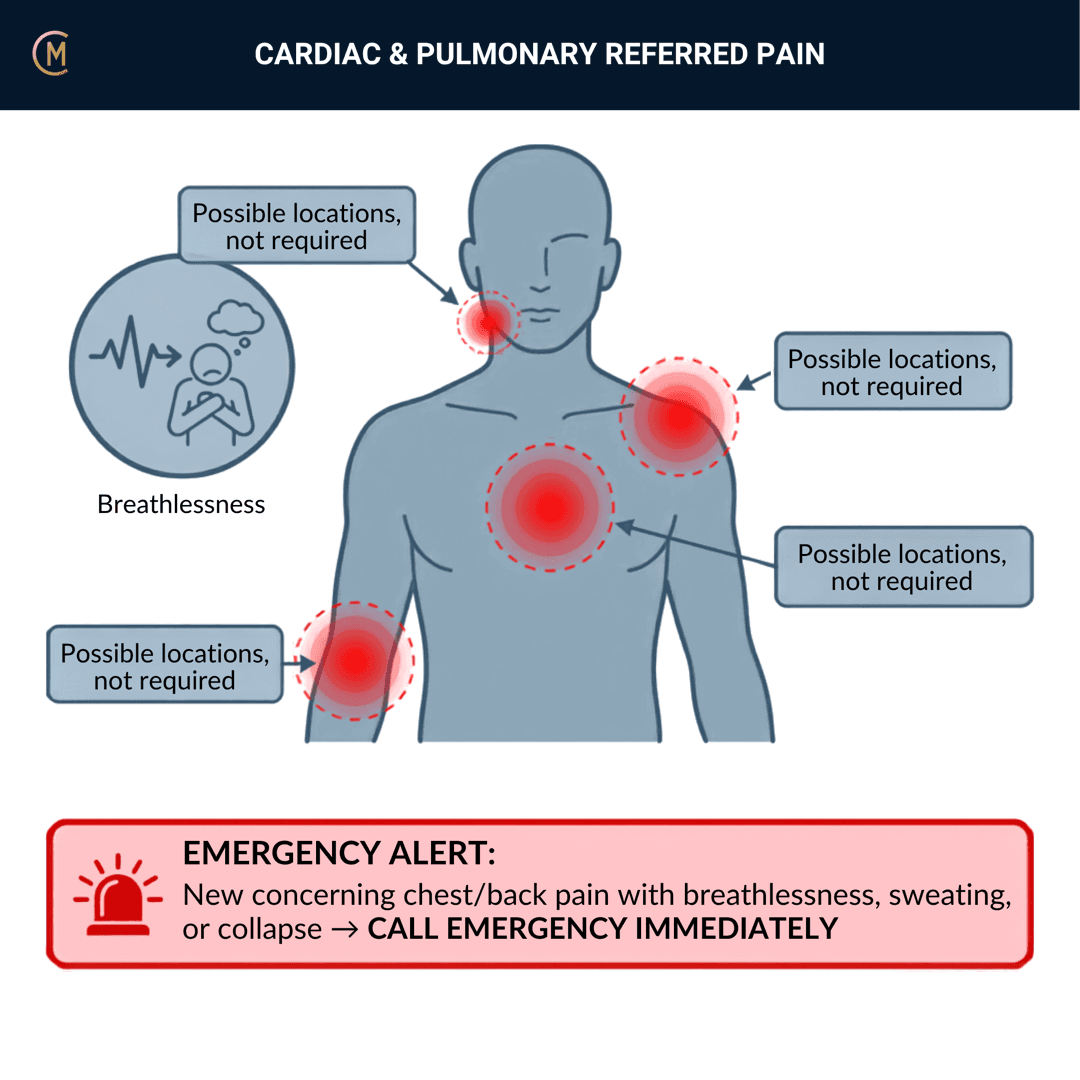
Who: Anyone with chest, upper back, shoulder or jaw pain. Including — especially — someone already discharged from an emergency department.
What: A visceral cause presenting as a musculoskeletal one.
How it behaves: Central or left chest ache ± neck, jaw, arm or back. Poor link to movement or posture. Associated: breathlessness, sweating, nausea, dizziness. Flags: night or rest pain, exertional onset, recent illness or immobility.
The one thing to take from this page:
"Not movement-provoked = not MSK until proven otherwise."
The one question, and the two branches
| Can you reproduce the pain with movement or palpation? | |
|---|---|
| YES | Probably musculoskeletal — but tenderness lowers probability, it does not exclude. Screen anyway. |
| NO | NOT MSK UNTIL PROVEN OTHERWISE. Vitals. Document your reasoning. Refer. |
Exertional → cardiac. Pleuritic + short of breath → pulmonary. Record the vitals before you refer.
2 · SE — THE SUBJECTIVE PATTERN (the 70%)
On this pattern the subjective is not 70% — it is essentially all of it. Five stages, and the special questions are the point.
MAIN PROBLEM
"There's a heaviness across my chest."
"It comes on when I walk up the hill and goes when I stop."
"I can't get a full breath."
BODY CHART
- Central or left chest, often diffuse — a hand, not a finger.
- Mark the neck, jaw, both arms and the interscapular region. Referral to jaw or arm changes everything.
- Mark the calf. Yes, on a chest pain history.
BEHAVIOUR — this is where it declares itself
| Visceral pattern | Musculoskeletal pattern | |
|---|---|---|
| Movement | No consistent link | Reproducible |
| Position | Doesn't change it | Changes it |
| Exertion | Brings it on, rest eases it | Usually load-related, not exertion-related |
| Palpation | Doesn't reproduce it | Often reproduces it |
| Breath | Pleuritic → pulmonary | Rib and joint patterns also catch with breath — so use the whole picture |
| Onset | Often abrupt, or with illness | Often an event or a load |
HISTORY
- Cardiac risk — age, hypertension, cholesterol, diabetes, smoking, family history, previous events.
- Recent immobility, long travel, surgery, plaster, pregnancy or postpartum, oestrogen-containing medication, known clotting disorder, active cancer.
- Recent respiratory illness.
- Have they already been assessed for this? Where, when, and what were they told? Being discharged from an emergency department is not clearance for a new or changed symptom.
SPECIAL / SCREENING QUESTIONS — never skipped, on any chest, upper back, jaw or shoulder presentation
- Any breathlessness, sweating, nausea, light-headedness?
- Does exertion bring it on and rest settle it?
- Any calf pain or swelling?
- Any fever, cough, coloured sputum, blood?
- Any pain at night or at rest that doesn't change with position?
- Have you fainted, or come close?
Assessing this region? Download the Thoracic Spine assessment template →
3 · HYPOTHESIS RANKING
On this page the ranking runs the other way. You are not ranking towards a diagnosis — you are ranking what you must not miss.
| What you must not miss | The feature that raises it |
|---|---|
| Acute coronary syndrome | Exertional onset settling with rest, central heaviness, radiation to jaw or arm, sweating, nausea. Presentations vary — complex and atypical ones are described [1][2]. |
| Pulmonary embolus | Pleuritic pain with breathlessness, calf symptoms, recent immobility, surgery, pregnancy or cancer. |
| Pneumonia or pleurisy | Fever, cough, coloured sputum, pleuritic pain. |
| Pneumothorax | Sudden breathlessness with sharp pleuritic pain, tall thin young adult or known lung disease. |
| Aortic pathology | Sudden severe tearing pain, front to back, unequal pulses. |
| Oesophageal and gastric causes | Relationship to meals, lying flat, reflux history. |
| Gallbladder and hepatobiliary | Right upper quadrant and right shoulder tip, relationship to food. |
| Herpes zoster | Dermatomal band, pre-eruptive pain, then rash. |
| Malignancy | Night pain, weight loss, smoking history, known cancer. |
And then the musculoskeletal patterns
Only after the above. Costochondritis · thoracic PIV joint · costovertebral and costotransverse · rib injury · cervical and shoulder girdle referral.
Note what this means: musculoskeletal chest pain is common, including in emergency department presentations [3][4]. Most chest pain isn't cardiac — and you still screen every time, because the cost of the two errors is not symmetrical.
4 · RED FLAGS — DON'T MISS THIS
This section is free, on every pattern, forever. On this page the whole thing is.
| Finding | What it suggests | What you do |
|---|---|---|
| Central or crushing chest pain with breathlessness, sweating, nausea, or radiation to jaw or arm | Acute coronary syndrome | 000. NOW. |
| Exertional onset settling with rest | Cardiac until proven otherwise | Same-day medical assessment |
| Sudden breathlessness with pleuritic pain, ± calf symptoms, immobility, surgery, pregnancy, cancer | Pulmonary embolus | EMERGENCY |
| Sudden severe tearing pain front to back, unequal pulses | Aortic dissection | 000 |
| Sudden pleuritic pain with breathlessness in a tall young adult or known lung disease | Pneumothorax | EMERGENCY |
| Fever, productive or bloody cough, hypoxia | Pneumonia, infection | Urgent medical review |
| Syncope or presyncope with chest pain | Cardiac or PE | EMERGENCY |
| Abnormal vital signs of any kind | Whatever the cause | Medical review |
| Pain not reproduced by any movement, position or palpation | Not musculoskeletal | Medical review — this is the whole rule |
| Night or rest pain unchanged by position | Visceral, infective, malignant | Medical review |
What to do, in order
- Stop. Don't treat.
- Sit them down. Take the vitals — heart rate, blood pressure, respiratory rate, oxygen saturation if you have a probe, temperature.
- Decide the tier: 000 · same-day emergency department · same-day GP · routine medical review.
- Write your reasoning down — the features present, the features absent, the vitals, and what you're asking to be excluded.
- Communicate it. Ring if it's urgent. Don't rely on the patient to relay it.
- Do not start musculoskeletal treatment while you wait.
Cross-links: Referred pain — visceral · Costochondritis / Tietze's · Thoracic facet (PIV) joint dysfunction · Rib contusion / stress injury
5 · OE — THE OBJECTIVE (the 30%)
Members
Sections 5 to 7 are for members
The objective exam, management and pearls, plus the six-minute lesson and the debrief. Free with an account.
Sign in or join free6 · MX — MANAGEMENT ESSENTIALS
Members
Sections 5 to 7 are for members
The objective exam, management and pearls, plus the six-minute lesson and the debrief. Free with an account.
Sign in or join free7 · CLINICAL PEARLS + RETRIEVAL CHECK
Members
Sections 5 to 7 are for members
The objective exam, management and pearls, plus the six-minute lesson and the debrief. Free with an account.
Sign in or join freeMembers
The 4-minute lesson is for members
Twelve slides on this pattern: what you'll hear, what to examine, what to do. Free with an account.
Sign in or join freeGuideline anchor
No Australian guideline for this presentation as a physiotherapy screening task.
More
The Australian anchor for the cardiac arm is the NHFA/CSANZ Australian Clinical Guideline for Diagnosing and Managing Acute Coronary Syndromes 2025 (Brieger et al. 2025, PMID 40180468), which the ACSQHC ACS Clinical Care Standard uses as its evidence base. The pulmonary embolism arm has the THANZ VTE guideline (Tran et al. 2019, PMID 30739331), which excludes VTE with a clinical prediction rule plus D-dimer and confirms it with imaging. Otherwise anchored to the emergency and primary-care literature on chest pain evaluation — acute coronary syndrome presentation and diagnostic evaluation (Barstow et al. 2020, PMID 32150364), contemporary approaches to pulmonary embolism diagnosis (Teissandier et al. 2024, PMID 38368878) and pulmonary embolism diagnosis and the D-dilemma (Horner et al. 2025, PMID 40360228) — with the Australasian prevalence work on musculoskeletal chest pain in emergency department presentations (Dacombe-Bird et al. 2024, PMID 38030390) and on reducing imaging for pulmonary embolism (Furyk et al. 2020, PMID 32023003).
None of this is a physiotherapy guideline and none of it tells you what to do in a clinic room. It is the medical literature about the thing you are screening for. Your task on this page is recognition and referral, not diagnosis — and nothing here replaces sending someone for medical assessment.
Members
The evidence summary is for members
Verified diagnostic accuracy, where the evidence stands and what it doesn't settle. Free with an account.
Sign in or join freeSources · 20
ShowHide
Every source on this page resolves and title-verifies against PubMed. Newest first.
- 2025Daas et al. (2025). A case report of complex acute coronary syndrome presentation: Plaque rupture and mild coronary artery ectasia presenting as de Winter T-waves morphing into anterior ST-elevation myocardial infarction in a young adult male. SAGE open medical case reports, 13, 2050313X251331733. https://doi.org/10.1177/2050313X251331733
- 2021Laher et al. (2021). Clinical Profile of Acute Coronary Syndrome Presentation to the Ladysmith Provincial Hospital: High Prevalence Among the Minority Indian Population. Cureus, 13(9), e17670. https://doi.org/10.7759/cureus.17670
- 2024Dacombe-Bird et al. (2024). Musculoskeletal chest pain prevalence in emergency department presentations: A retrospective case notes review. Emergency medicine Australasia : EMA, 36(2), 302-309. https://doi.org/10.1111/1742-6723.14352
- 2021Mandrekar et al. (2021). Prevalence of musculoskeletal chest pain in the emergency department: a systematic review and meta-analysis. Scandinavian journal of pain, 21(3), 434-444. https://doi.org/10.1515/sjpain-2020-0168
- 2025Horner & Roberts (2025). Pulmonary embolism diagnosis and the D-dilemma. Emergency medicine journal : EMJ, 42(8), 560-561. https://doi.org/10.1136/emermed-2025-215058
- 2024Teissandier et al. (2024). Contemporary approaches to pulmonary embolism diagnosis: a clinical review. Clinical and experimental emergency medicine, 11(2), 127-135. https://doi.org/10.15441/ceem.23.157
- 2023Khandait et al. (2023). Acute pulmonary embolism: Diagnosis and management. Indian heart journal, 75(5), 335-342. https://doi.org/10.1016/j.ihj.2023.05.007
- 2026Ádám et al. (2026). [Development of a novel clinical prediction model for musculoskeletal chest pain in the emergency department]. Orvosi hetilap, 167(5), 180-187. https://doi.org/10.1556/650.2026.33484
- 2020Richardson et al. (2020). Predictors of Overtesting in Pulmonary Embolism Diagnosis. Academic radiology, 27(3), 404-408. https://doi.org/10.1016/j.acra.2019.04.018
- 2020Furyk & Banks (2020). Reducing imaging for pulmonary embolism diagnosis. Emergency medicine Australasia : EMA, 32(1), 176-178. https://doi.org/10.1111/1742-6723.13459
- 2022Aghajani et al. (2022). Predictors and mortality of patients with delayed pulmonary embolism diagnosis: A cohort study. Caspian journal of internal medicine, 13(4), 757-764. https://doi.org/10.22088/cjim.13.4.757
- 2016Bach et al. (2016). Timing of pulmonary embolism diagnosis in the emergency department. Thrombosis research, 137, 53-57. https://doi.org/10.1016/j.thromres.2015.11.019
- 2012Stochkendahl et al. (2012). A randomized clinical trial of chiropractic treatment and self-management in patients with acute musculoskeletal chest pain: 1-year follow-up. Journal of manipulative and physiological therapeutics, 35(4), 254-62. https://doi.org/10.1016/j.jmpt.2012.04.003
- 2008Stochkendahl et al. (2008). Diagnosis and treatment of musculoskeletal chest pain: design of a multi-purpose trial. BMC musculoskeletal disorders, 9, 40. https://doi.org/10.1186/1471-2474-9-40
- 2016Stochkendahl et al. (2016). Cost-effectiveness of chiropractic care versus self-management in patients with musculoskeletal chest pain. Open heart, 3(1), e000334. https://doi.org/10.1136/openhrt-2015-000334
- 2017Gelfman (2017). Osteopathic Manipulation in Treatment of Musculoskeletal Chest Pain. The American journal of medicine, 130(6), 618. https://doi.org/10.1016/j.amjmed.2016.11.046
- 2013Ayloo et al. (2013). Evaluation and treatment of musculoskeletal chest pain. Primary care, 40(4), 863-87, viii. https://doi.org/10.1016/j.pop.2013.08.007
- 2020Liti et al. (2020). Clinical effectiveness of an outpatient pathway for low-risk chest pain emergency department visits. Journal of nuclear cardiology : official publication of the American Society of Nuclear Cardiology, 27(4), 1341-1348. https://doi.org/10.1007/s12350-019-01814-9
- 2020Barstow (2020). Acute Coronary Syndrome: Presentation and Diagnostic Evaluation. FP essentials, 490, 11-19. PubMed 32150364
- 2024Gottlieb et al. (2024). Epidemiology of pulmonary embolism diagnosis and management among United States emergency departments over an eight-year period. The American journal of emergency medicine, 85, 158-162. https://doi.org/10.1016/j.ajem.2024.09.016
Mapped to this pattern
Generic measures that also apply
- Borg RPE
Borg Rating of Perceived Exertion Scale (6-20)
perceived exertion · 1 items · 1 min
- GROC
Global Rating of Change Scale
perceived change since baseline · 1 items · 1 min
- NPRS
Numeric Pain Rating Scale
pain intensity · 1 items · 1 min
- PGIC
Patient Global Impression of Change
perceived change since baseline · 1 items · 1 min
- PSFS
Patient-Specific Functional Scale
patient-generated function · 3 items · 2 min
- SANE
Single Assessment Numeric Evaluation
patient-rated function as a percentage of normal · 1 items · 1 min
- VAS
Visual Analogue Scale
pain intensity · 1 items · 1 min
- Borg CR10
Borg Category Ratio 10 Scale
perceived exertion or symptom intensity, ratio scale · 1 items · 1 min
- GAS
Goal Attainment Scaling
individualised goal achievement · 10 min
Did this page do its job?
CliniStudy is in beta. One tap is enough — it decides what gets fixed first.