
1 · SNAPSHOT
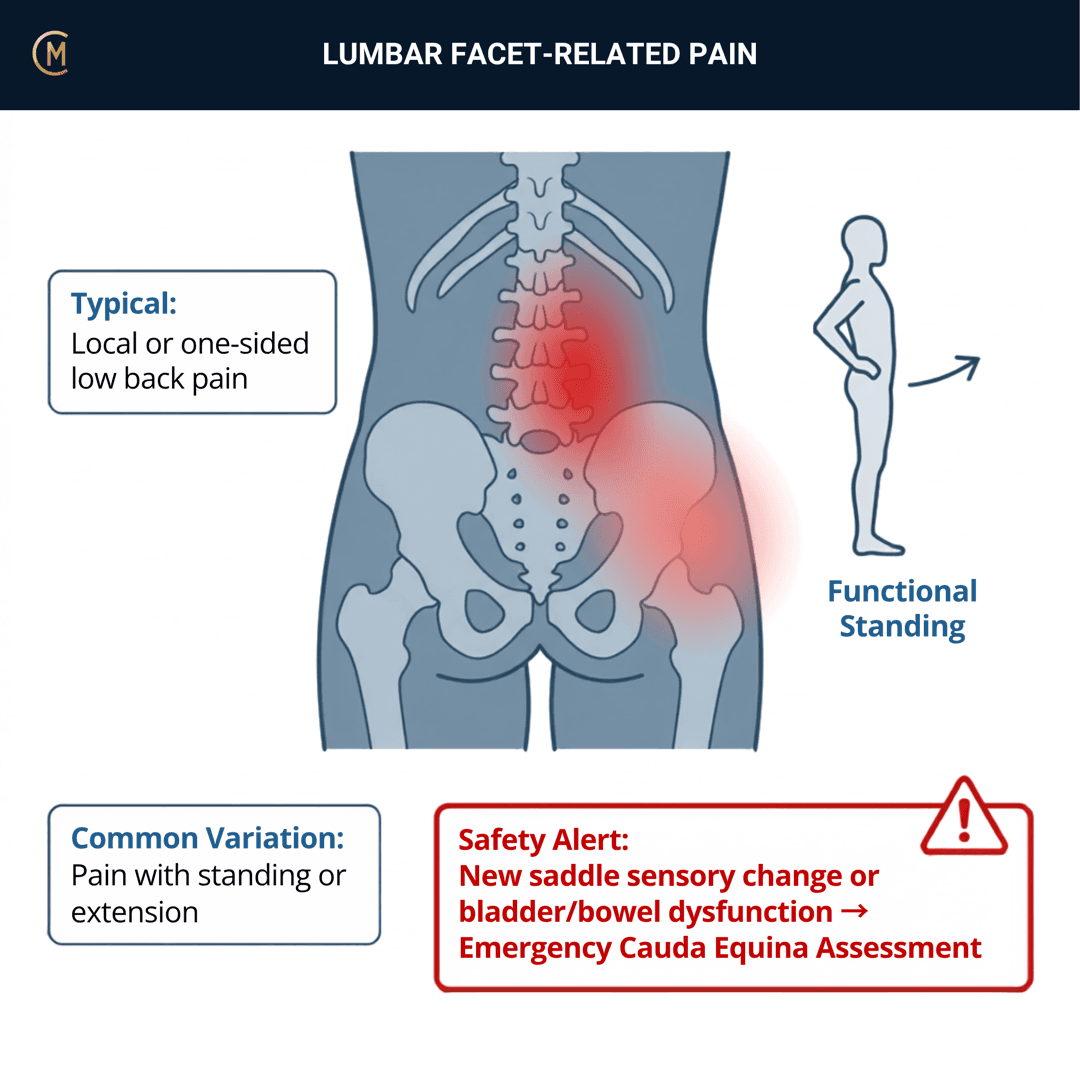
Naming first, because it costs marks and wastes search time. UniSA teaches this joint as the PIV joint — the posterior intervertebral joint. The literature calls the same structure the lumbar facet joint or the lumbar zygapophysial joint (also spelled zygapophyseal). PubMed holds zero records using the string "PIV joint". Write PIV joint in your notes; search lumbar zygapophysial, lumbar zygapophyseal, lumbar facet joint and medial branch block when you go looking. Same joint every time.
Who: Anyone with a lumbar spine. Often after an awkward movement, a rotation or a lifting incident — though no study has ever tested onset mechanism against a block.
What: Localised, unilateral, non-midline lumbar pain ± non-dermatomal referral into the buttock or proximal thigh. No root-level neurological deficit.
How it behaves: Aggs: extension, side flexion, rotation, sustained standing. Eases: rest, recumbency, flexion, gentle movement.
The illness script in one line:
One segment's posterior joint made sore and stiff — so the pain sits off the midline on one side, may spill into the buttock without following a dermatome, settles when they lie down, and comes back under your thumb at a single level.
The one thing to take from this page — and read it next to the cervical page, because the contrast is the lesson:
You cannot carry cervical confidence into a lumbar spine. In the neck, manual segmental examination against controlled blocks pools at sensitivity 0.91, specificity 0.74 [1]. In the low back, two Australian-led systematic reviews sixteen years apart could not find a single clinical examination test that clears the informativeness bar [2][3]. Same technique. Same reference standard. Different answer.
| Figure | Number |
|---|---|
| People living with low back pain worldwide, 2020 | 619 million (95% UI 554–694), projected 843 million by 2050 |
| Facet-mediated pain, dual diagnostic blocks, 18 studies | 16%–45%, Level I — the strongest evidence base in the spine |
| Largest modern series, controlled comparative blocks | 34.1% (95% CI 28.8–39.8) |
| The same patients, single uncontrolled block | 67.9% (62.9–73.2) |
| "Pure" Z joint pain, complete relief under placebo control | 15% (10–20%), n=206 |
| False-positive rate of a single block | 25%–50% across 18 studies · 49.8% (42.7–56.8) in the largest series · 38% with PPV 31% in the foundational Australian cohort |
| Clinical examination tests that clear +LR ≥2 or −LR ≤0.5 | None. 8 facet studies in 2007. 14 facet studies in 2023 |
| The only informative index test of any kind | SPECT uptake — +LR 2.80 (1.82–4.31), −LR 0.44 (0.25–0.77), n=121 |
| Best clinical rule ever published | +LR 9.7 — derivation only, never validated, 95% relief standard, single uncontrolled block |
| Community facet joint OA on CT | 59.6% of men · 66.7% of women · 89.2% at 60–69 · no association with low back pain |
| Facet joint degeneration in asymptomatic elite junior tennis players | 24% (n=25) |
(GBD 2021 [4] [5] [6] [7] [8] [2] [3] [9] [10] [11].)
✅ Australia HAS a guideline for this patient — and it mentions this structure exactly once, to tell you not to over-read it. The Low Back Pain Clinical Care Standard (ACSQHC 2022) covers everyone who walks in with this presentation. It recognises two things that are not simply "low back pain": radicular pain/sciatica, and specific or serious pathology. There is no facet, zygapophysial or PIV joint subgroup anywhere in it.
The only place facet joints appear is Quality statement 3, where clinicians are told to advise the patient that findings such as disc degeneration, facet joint arthritis and disc bulges are "very common in people without pain and are usually a normal feature of ageing". Verified live at safetyandquality.gov.au on 2 Sep 2026.
That is the Australian position on this structure, and it is a gift to the page rather than an embarrassment — it is exactly what Kalichman et al. (2008) and Connolly et al. (2020) measured. Meanwhile the only guideline-shaped documents that name this pattern are interventional pain medicine — controlled blocks, image guidance, radiofrequency ablation after confirmation [12]. Not one line of it is physiotherapy.
Patterns > Labels. "L4-5 facet joint" names a structure you cannot confirm. Unilateral, non-midline, one level, comparable sign, nothing radicular names the problem you can treat on Monday. Manage it as non-specific low back pain until something changes that — and check it with your educator.
2 · SE — THE SUBJECTIVE PATTERN (the 70%)
Five stages, in order. And the honest opening, because it is a finding rather than a failure: the subjective does less diagnostic work on this page than on almost any other.
- In 176 consecutive chronic low back pain patients taken to controlled blocks, "response to zygapophysial joint injection was not associated with any single clinical feature or set of clinical features" [13]. The authors' conclusion in the same abstract: the joint is an important source of pain, but "the existence of a 'facet syndrome' must be questioned".
- In 200 more, in a different country and a different practice type: "the history, clinical features, and radiological features are of no significance or assistance in making the diagnosis of facet joint mediated pain with certainty" [14].
Two studies, 376 patients, same answer. So the subjective here does what a subjective is actually for. It generates a level hypothesis, sets your dosage, and rules out the neighbours. It does not name the joint.
MAIN PROBLEM
"It's down low on the right, right there. Started when I twisted lifting a box on Thursday. Aches into my backside when I've been standing a while. Nothing down the leg, no pins and needles."
Listen for one spot, one side, off the midline, and nothing radicular. Ask them to point with one finger. If they smear a whole hand across the low back and cannot keep it in one place, you are on the non-specific low back pain page — which, on this pattern, is where most of them stay.
BODY CHART
- P1: unilateral, non-midline, low lumbar, at one or two levels. P2 commonly into the buttock and occasionally the proximal thigh. Draw P+ / P++ where they show you the worst of it and mark the side clearly. Check and mark both sides.
- Referral is real, and it does not exclude this pattern. Stimulating the L1-2 to L5-S1 joints and the L1–L5 medial branches in 48 patients produced referral mapped to six areas — and the distributions were "similar for each level stimulated" with "considerable" overlap between levels [15]. No accuracy statistic exists in that paper; do not quote one from it.
- So the body chart gives you a region, never a level and never a source. That is a sharper limit than the neck, where a pain diagram picked the level at the first attempt in 83% of an Australian audit. There is no lumbar equivalent of that finding.
- Anything dermatomal, below the knee, or with paraesthesia is a different page — lumbar radicular pain.
BEHAVIOUR
- Aggs: extension, side flexion, rotation, sustained standing, walking on hard ground, the movement that started it, rising from a chair after sitting a while.
Eases: rest, recumbency, flexion, gentle movement, unloading. - 24-hr pattern: sustained standing and walking on hard ground build it; recumbency and flexion ease it; rising from a chair after sitting a while is in the Aggs. Morning stiffness under 30 minutes = M.
- Night: recumbency relieves it — the pattern's own line. Night pain that is progressive and constant is a §4 flag; over 30 minutes of morning stiffness with night pain in a young patient re-asks the inflammatory questions.
- Severity: VAS 0–10 at best / at worst / right now.
- "Well relieved by recumbency" is the single history item that has appeared in every published criteria set for this joint [16]. Ask it directly. Write the answer down.
- And then the inversion nobody teaches. The one measured positive from a blinded physiotherapist examination in this literature is that lumbar zygapophysial joint pain went with the ABSENCE of pain when rising from sitting ([17], n=81, reported as associations rather than accuracy). Pain on rising from sitting pointed at the disc, not the joint. The strongest history features in this whole literature are things that don't hurt.
- Coding: usually In — intermittent, position- and movement-driven — moving to P when irritable and back to Is as it settles. Morning stiffness <30 min = M; >30 min = In, and >30 min in a young patient with bilateral symptoms and night pain should make you re-ask the inflammatory questions.
- Irritability decides your dosage, and it has three parts. Resting symptoms? How vigorous is the activity that provokes it? How long does it take to settle? High irritability = Grades I–II to P1 only, no overpressure (o.p.), no quadrant test and no combined-movement provocation on day one. You are choosing a technique from this answer, not from a diagnosis.
HISTORY
- Onset: an awkward movement, a rotation, a lifting incident — or nothing at all. Date it and date what it has done since. Note honestly that no study has ever tested onset mechanism against a block.
- Previous episodes, previous imaging, what they have been told, and what helped last time. If they arrive with a report saying "facet joint arthropathy", section 5 tells you what to do with it, and the Australian Standard tells you what to say about it.
- Read the prevalence literature knowing where it came from. Every figure on this page comes from chronic, refractory, tertiary-referred patients who agreed to be injected. Han et al. (2023) flag it themselves: most included studies used convenience samples referred to tertiary settings, which may inflate prevalence estimates. Nobody has estimated the proportion of acute primary-care low back pain that is PIV joint pain, because nobody is going to inject that population.
SPECIAL / SCREENING QUESTIONS
Every patient. Every time. Before you touch them.
- Cauda equina: bladder or bowel change, saddle anaesthesia, bilateral leg symptoms, progressive weakness. Same-day, no exceptions. Cauda equina syndrome.
- Fracture, malignancy, infection: trauma, contusion or abrasion, prolonged corticosteroid use, cancer history, unexplained weight loss, fever, IV drug use, night pain that is progressive and constant. Escalate on the cluster — section 4.
- Radicular pain: leg-dominant pain below the knee, dermatomal band, paraesthesia, numbness, myotomal weakness. Run the neurological examination the ACSQHC Standard prescribes — straight leg raise, deep tendon reflexes, strength and sensation — and go to lumbar radicular pain.
- Stenosis: bilateral leg heaviness on walking and standing, eased by sitting or flexion, the "shopping trolley sign", typically >60 years. Lumbar spinal canal stenosis.
- The adolescent extension athlete: unilateral extension pain in an adolescent playing an extension- and rotation-loaded sport looks exactly like this pattern. Medical review before you load extension — section 3 says why.
Assessing this region? Download the Lumbar Spine & SIJ assessment template →
3 · HYPOTHESIS RANKING
Rank the mechanical patterns — then rule out the dangerous ones first, in section 4. One discriminating feature each. That is all you need to move between them.
| # | Competing pattern | The one discriminating feature |
|---|---|---|
| 1 | Non-specific low back pain | Diffuse or ill-localised — a smear, not a spot. It will not stay at one level with a comparable sign on unilateral PAIVMs. This is the pattern next door and it is the default, not the fallback — given that no clinical test separates a PIV joint source at all, the honest split is how you organise the examination, not what you call the tissue. Non-specific low back pain. |
| 2 | Lumbar discogenic pain | Central or bilateral deep ache, worse sitting and flexion, eased standing or lying, flexion limited more than extension, reproduced by central PAIVMs. The measured discriminator is centralisation on repeated movements: +LR 2.8 (95% CI 1.4–5.3) for the disc [2] — and centralisation was not associated with a positive Z joint block response at any relief standard [9]. |
| 3 | Lumbar radicular pain / radiculopathy | Leg-dominant, below-knee, dermatomal pain ± myotomal weakness, reflex change, positive SLR or slump. PIV joint pain refers non-dermatomally and produces no root-level deficit. Lumbar radicular pain — do not re-use its numbers. |
Then the three you must be able to name in a viva.
- Sacroiliac joint pain — the one lumbopelvic structure with a clinical test that works. A composite of ≥3 positive provocation tests: +LR 2.44 (95% CI 1.50–3.98), −LR 0.31 (0.21–0.47), 6 studies pooled; absence of midline low back pain +LR 2.41 (1.89–3.07) [3]. If your unilateral, non-midline pain is below L5 and the provocation tests stack up, the SIJ is a better-evidenced hypothesis than the PIV joint. SIJ dysfunction.
- Lumbar spinal canal stenosis. Bilateral leg heaviness on walking and standing, eased by sitting or flexion, typically >60 years. And notice this: Petersen et al. [18] built usable best-evidence diagnostic rules for the disc, SIJ, spondylolisthesis, disc herniation with nerve root involvement and spinal stenosis. They could not build one for the facet joint. Lumbar spinal canal stenosis.
- Spondylolysis / pars stress injury. Adolescent, extension- and rotation-loaded sport, unilateral extension pain — it looks exactly like this pattern. In 25 asymptomatic elite junior tennis players, 36% had pars abnormalities, 24% bone marrow oedema and 24% facet joint degeneration [11]. In this age group with this pain, medical review before you load extension.
And the honesty caveat that belongs at the bottom of this table. The most current attempt to define this pattern for primary care is a modified Delphi consensus — 2,682 articles screened, 8 used, 77 items, 39 orthopaedic spine surgeons, four criteria produced [19]. No sensitivity, specificity or likelihood ratio is reported and it was not validated against blocks. Thirty years after Schwarzer, the field is still defining this pattern by expert opinion. Cite it for the state of the field, never for a number.
Rank the mechanical ones. Rule out the dangerous ones first. Section 4 decides whether you are allowed to treat at all.
4 · RED FLAGS — DON'T MISS THIS
This section is free, on every pattern, forever. Safety is never gated, and it never will be.
Cauda equina — same day, no exceptions
Bladder or bowel change · saddle anaesthesia · bilateral leg symptoms · progressive weakness. These features are specific, not sensitive — their absence does not clear it. The ACSQHC Low Back Pain Clinical Care Standard names cauda equina as an emergency referral trigger in Quality statement 1.
Learn it properly on the cauda equina syndrome page. It is not restated here, and that is deliberate — one page owns it, and that page is free too.
Fracture, malignancy, infection — escalate on the cluster, not the checklist
Guidelines carry 53 red flags. Most of them "provide virtually no change in probability" of fracture or malignancy, or have never had their accuracy tested at all. The ones that shift the number, as post-test probabilities ([20], 14 studies):
| Flag | Post-test probability |
|---|---|
| Multiple red flags present | 90% (95% CI 34–99) — fracture |
| Contusion or abrasion | 62% (49–74) — fracture |
| Prolonged corticosteroid use | 33% (10–67) — fracture |
| History of malignancy | 33% (22–46) — malignancy |
| Severe trauma | 11% (8–16) — fracture |
| Older age | 9% (3–25) — fracture |
One flag is a question. A cluster is a referral.
Know the base rate before you panic
Across 22 studies and 41,320 patients presenting to emergency departments with low back pain, the prevalence of any pathology requiring immediate or urgent treatment was 2.5%–5.1% (prospective): vertebral fracture 0.0–7.2%, spinal cancer 0.0–2.1%, infection 0.0–1.9%, cord or cauda equina compression 0.1–1.9%, vascular 0.0–0.9%. The diagnostic accuracy of most red flags rests on a single study each [21]. That is an ED population. In a clinic it is lower still.
The neurological screen
Run it, record it, date it: power, reflexes AND sensation — bilaterally, plus straight leg raise where leg symptoms are present. This is the examination the ACSQHC Standard prescribes in Quality statement 1. Normal is what you expect in this pattern. You do it to exclude the neighbours, not to confirm the joint — and an undated normal is worth nothing when you need a baseline in three weeks.
What to do
| Trigger | Urgency |
|---|---|
| Any cauda equina feature | Same day. No exceptions |
| Progressive neurological deficit | Urgent medical referral |
| A cluster of fracture, malignancy or infection flags | Medical review, imaging |
| Severe trauma, contusion or abrasion, prolonged corticosteroid use | Medical review |
| Night pain that is progressive and constant, fever, unexplained weight loss, cancer history | Medical review |
Bladder + saddle = surgical emergency.
If progressive weakness → refer immediately.
5 · OE — THE OBJECTIVE (the 30%)
Members
Sections 5 to 7 are for members
The objective exam, management and pearls, plus the six-minute lesson and the debrief. Free with an account.
Sign in or join free6 · MX — MANAGEMENT ESSENTIALS
Members
Sections 5 to 7 are for members
The objective exam, management and pearls, plus the six-minute lesson and the debrief. Free with an account.
Sign in or join free7 · CLINICAL PEARLS + RETRIEVAL CHECK
Members
Sections 5 to 7 are for members
The objective exam, management and pearls, plus the six-minute lesson and the debrief. Free with an account.
Sign in or join freeMembers
The 4-minute lesson is for members
Twelve slides on this pattern: what you'll hear, what to examine, what to do. Free with an account.
Sign in or join freeGuideline anchor
Low Back Pain Clinical Care Standard (ACSQHC 2022) — the same Australian anchor as the non-specific low back pain and lumbar radicular pain pages.
More
Read honestly: the Standard covers this patient and does NOT recognise the PIV/facet joint as a subgroup. It names exactly two things that are not simply 'low back pain' — radicular pain/sciatica, and specific or serious pathology. Facet joints appear once in the whole document, in Quality statement 3, where clinicians are told to advise patients that 'facet joint arthritis' is 'very common in people without pain' and 'usually a normal feature of ageing'. An Australian standard that recognises this structure only to tell you not to over-read it. Verified live against safetyandquality.gov.au on 2 Sep 2026.
Australia has a Standard, it covers this patient, and it deliberately does not carry this label. Both halves go on the page.
Members
The evidence summary is for members
Verified diagnostic accuracy, where the evidence stands and what it doesn't settle. Free with an account.
Sign in or join freeSources · 32
ShowHide
Every source on this page resolves and title-verifies against PubMed. Newest first.
- 2018Usunier et al. (2018). Clinical Diagnostic Tests versus Medial Branch Blocks for Adults with Persisting Cervical Zygapophyseal Joint Pain: A Systematic Review and Meta-Analysis. Physiotherapy Canada. Physiotherapie Canada, 70(2), 179-187. https://doi.org/10.3138/ptc.2016-89.mt
- 2007Hancock et al. (2007). Systematic review of tests to identify the disc, SIJ or facet joint as the source of low back pain. European spine journal : official publication of the European Spine Society, the European Spinal Deformity Society, and the European Section of the Cervical Spine Research Society, 16(10), 1539-50. https://doi.org/10.1007/s00586-007-0391-1
- 2023Han et al. (2023). Low back pain of disc, sacroiliac joint, or facet joint origin: a diagnostic accuracy systematic review. EClinicalMedicine, 59, 101960. https://doi.org/10.1016/j.eclinm.2023.101960
- 2023Anon. (2023). Global, regional, and national burden of low back pain, 1990-2020, its attributable risk factors, and projections to 2050: a systematic analysis of the Global Burden of Disease Study 2021. The Lancet. Rheumatology, 5(6), e316-e329. https://doi.org/10.1016/S2665-9913(23)00098-X
- 2026Manchikanti et al. (2026). An Updated (2026) Best-Evidence Synthesis Appraisal of the Diagnostic Accuracy and Utility of Facet (Zygapophysial) Joint Injections in Chronic Spinal Pain. Pain physician, 29(4S), S229-S271. PubMed 42370931
- 2020Manchikanti et al. (2020). Low Back Pain and Diagnostic Lumbar Facet Joint Nerve Blocks: Assessment of Prevalence, False-Positive Rates, and a Philosophical Paradigm Shift from an Acute to a Chronic Pain Model. Pain physician, 23(5), 519-530. PubMed 32967394
- 1994Schwarzer et al. (1994). The false-positive rate of uncontrolled diagnostic blocks of the lumbar zygapophysial joints. Pain, 58(2), 195-200. https://doi.org/10.1016/0304-3959(94)90199-6
- 2021MacVicar et al. (2021). The Prevalence of "Pure" Lumbar Zygapophysial Joint Pain in Patients with Chronic Low Back Pain. Pain medicine (Malden, Mass.), 22(1), 41-48. https://doi.org/10.1093/pm/pnaa383
- 2006Laslett et al. (2006). Clinical predictors of screening lumbar zygapophyseal joint blocks: development of clinical prediction rules. The spine journal : official journal of the North American Spine Society, 6(4), 370-9. https://doi.org/10.1016/j.spinee.2006.01.004
- 2008Kalichman et al. (2008). Facet joint osteoarthritis and low back pain in the community-based population. Spine, 33(23), 2560-5. https://doi.org/10.1097/BRS.0b013e318184ef95
- 2020Connolly et al. (2020). Lumbar spine abnormalities and facet joint angles in asymptomatic elite junior tennis players. Sports medicine - open, 6(1), 57. https://doi.org/10.1186/s40798-020-00285-4
- 2025Sebastian et al. (2025). Consensus-Based Interventions for Cervical and Lumbar Facet Joint Pain and Sacroiliac Joint Disorders: A Concise Summary of International Practice Guidelines. Cureus, 17(12), e98977. https://doi.org/10.7759/cureus.98977
- 1994Schwarzer et al. (1994). Clinical features of patients with pain stemming from the lumbar zygapophysial joints. Is the lumbar facet syndrome a clinical entity?. Spine, 19(10), 1132-7. https://doi.org/10.1097/00007632-199405001-00006
- 2000Manchikanti et al. (2000). The inability of the clinical picture to characterize pain from facet joints. Pain physician, 3(2), 158-66. PubMed 16906195
- 1997Fukui et al. (1997). Distribution of referred pain from the lumbar zygapophyseal joints and dorsal rami. The Clinical journal of pain, 13(4), 303-7. https://doi.org/10.1097/00002508-199712000-00007
- 1998Revel et al. (1998). Capacity of the clinical picture to characterize low back pain relieved by facet joint anesthesia. Proposed criteria to identify patients with painful facet joints. Spine, 23(18), 1972-6; discussion 1977. https://doi.org/10.1097/00007632-199809150-00011
- 2003Young et al. (2003). Correlation of clinical examination characteristics with three sources of chronic low back pain. The spine journal : official journal of the North American Spine Society, 3(6), 460-5. https://doi.org/10.1016/s1529-9430(03)00151-7
- 2017Petersen et al. (2017). Clinical classification in low back pain: best-evidence diagnostic rules based on systematic reviews. BMC musculoskeletal disorders, 18(1), 188. https://doi.org/10.1186/s12891-017-1549-6
- 2026Abe et al. (2026). Expert Consensus-Based Criteria for Identifying Lumbar Facet Joint Pain in Primary Care: Development Using Factor Analysis and a Modified Delphi Method. Pain and therapy, 15(1), 235-249. https://doi.org/10.1007/s40122-025-00788-6
- 2013Downie et al. (2013). Red flags to screen for malignancy and fracture in patients with low back pain: systematic review. BMJ (Clinical research ed.), 347, f7095. https://doi.org/10.1136/bmj.f7095
- 2020Galliker et al. (2020). Low Back Pain in the Emergency Department: Prevalence of Serious Spinal Pathologies and Diagnostic Accuracy of Red Flags. The American journal of medicine, 133(1), 60-72.e14. https://doi.org/10.1016/j.amjmed.2019.06.005
- 2004Laslett et al. (2004). Zygapophysial joint blocks in chronic low back pain: a test of Revel's model as a screening test. BMC musculoskeletal disorders, 5, 43. https://doi.org/10.1186/1471-2474-5-43
- 2014Hidalgo et al. (2014). Intertester agreement and validity of identifying lumbar pain provocative movement patterns using active and passive accessory movement tests. Journal of manipulative and physiological therapeutics, 37(2), 105-15. https://doi.org/10.1016/j.jmpt.2013.09.006
- 2004Seffinger et al. (2004). Reliability of spinal palpation for diagnosis of back and neck pain: a systematic review of the literature. Spine, 29(19), E413-25. https://doi.org/10.1097/01.brs.0000141178.98157.8e
- 1995Schwarzer et al. (1995). The ability of computed tomography to identify a painful zygapophysial joint in patients with chronic low back pain. Spine, 20(8), 907-12. https://doi.org/10.1097/00007632-199504150-00005
- 2019Rubinstein et al. (2019). Benefits and harms of spinal manipulative therapy for the treatment of chronic low back pain: systematic review and meta-analysis of randomised controlled trials. BMJ (Clinical research ed.), 364, l689. https://doi.org/10.1136/bmj.l689
- 2021Hayden et al. (2021). Exercise therapy for chronic low back pain. The Cochrane database of systematic reviews, 9(9), CD009790. https://doi.org/10.1002/14651858.CD009790.pub2
- 2008Hancock et al. (2008). Independent evaluation of a clinical prediction rule for spinal manipulative therapy: a randomised controlled trial. European spine journal : official publication of the European Spine Society, the European Spinal Deformity Society, and the European Section of the Cervical Spine Research Society, 17(7), 936-43. https://doi.org/10.1007/s00586-008-0679-9
- 2017Juch et al. (2017). Effect of Radiofrequency Denervation on Pain Intensity Among Patients With Chronic Low Back Pain: The Mint Randomized Clinical Trials. JAMA, 318(1), 68-81. https://doi.org/10.1001/jama.2017.7918
- 2015Maas et al. (2015). Radiofrequency denervation for chronic low back pain. The Cochrane database of systematic reviews, 2015(10), CD008572. https://doi.org/10.1002/14651858.CD008572.pub2
- 2026Truong et al. (2026). Current evidence on radiofrequency denervation for chronic low back pain: a systematic review and meta-analysis. BMJ open, 16(7), e105106. https://doi.org/10.1136/bmjopen-2025-105106
- 1994Schwarzer et al. (1994). The relative contributions of the disc and zygapophyseal joint in chronic low back pain. Spine, 19(7), 801-6. https://doi.org/10.1097/00007632-199404000-00013
Mapped to this pattern
Generic measures that also apply
- Borg RPE
Borg Rating of Perceived Exertion Scale (6-20)
perceived exertion · 1 items · 1 min
- GROC
Global Rating of Change Scale
perceived change since baseline · 1 items · 1 min
- NPRS
Numeric Pain Rating Scale
pain intensity · 1 items · 1 min
- PGIC
Patient Global Impression of Change
perceived change since baseline · 1 items · 1 min
- PSFS
Patient-Specific Functional Scale
patient-generated function · 3 items · 2 min
- SANE
Single Assessment Numeric Evaluation
patient-rated function as a percentage of normal · 1 items · 1 min
- VAS
Visual Analogue Scale
pain intensity · 1 items · 1 min
- Borg CR10
Borg Category Ratio 10 Scale
perceived exertion or symptom intensity, ratio scale · 1 items · 1 min
- GAS
Goal Attainment Scaling
individualised goal achievement · 10 min
Did this page do its job?
CliniStudy is in beta. One tap is enough — it decides what gets fixed first.