
1 · SNAPSHOT
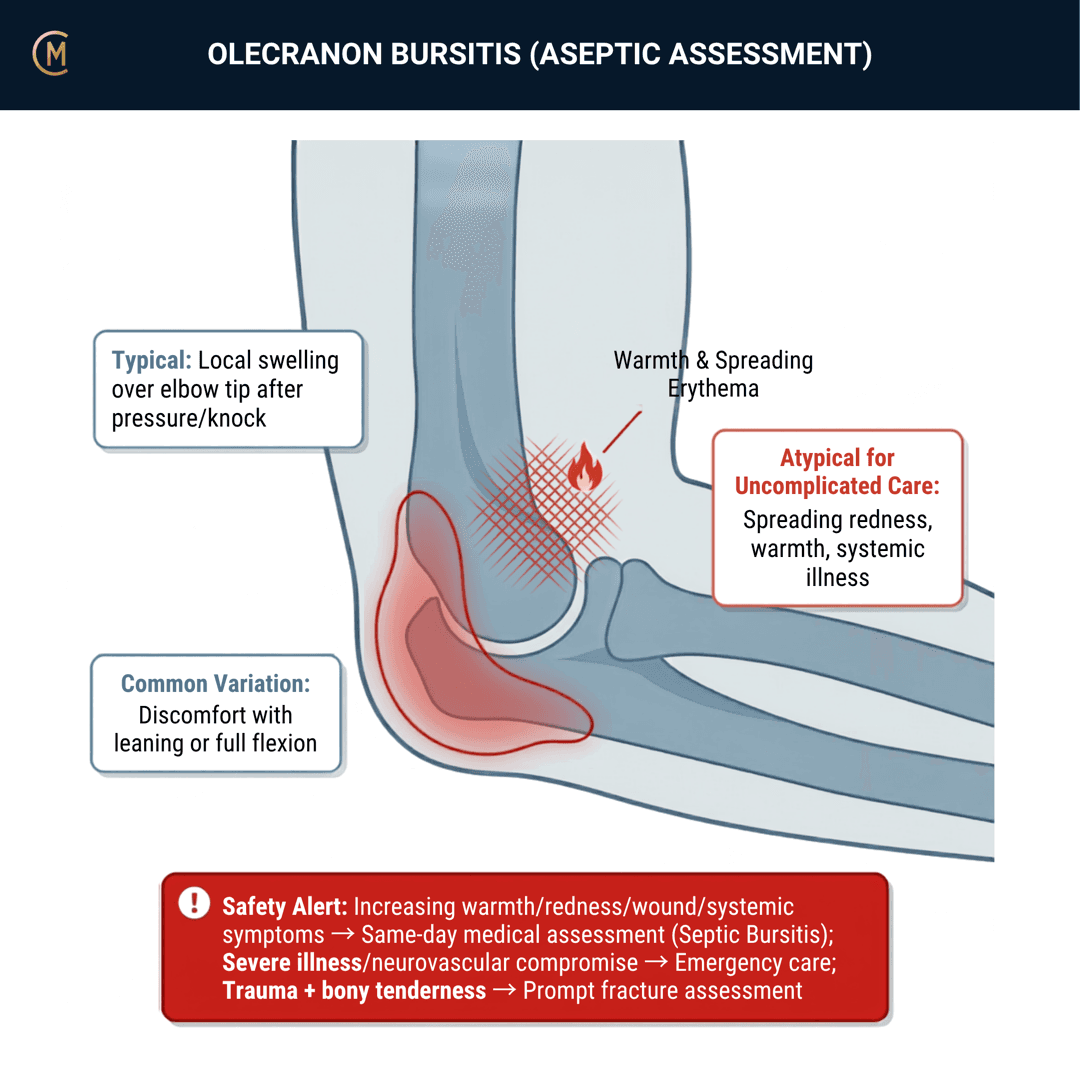
Visually alarming, usually benign, and the two tempting treatments are the two that cause the trouble.
Illness script in one line: a localised, often dramatic swelling over the point of the elbow that hurts far less than it looks, following a knock, a fall, or weeks of leaning on a desk or a floor — with full but uncomfortable end-range flexion and an otherwise normal elbow.
Caseload frequency: common enough that you'll see it on placement. Read further: risk factors in a large-scale population-based study [1], trauma-related cases [2][3], superficial bursitis [4].
The bursa is superficial, and everything you put through the skin costs something
This is the organising idea, and it reverses the instinct. The olecranon bursa sits directly under thin, mobile, poorly vascularised skin with bone immediately behind it. Aspirating it and injecting it both feel like doing something. Both cross that skin.
And the boring option has actually been randomised. Read further: a randomised trial of compression plus non-steroidal anti-inflammatory drugs and other approaches [5], a commentary on it [6], non-surgical treatment of aseptic olecranon bursitis [7], treatment [8].
The reframe:
| The instinct | The better position |
|---|---|
| "It's full of fluid — drain it" | Compression has a randomised trial. Aspiration doesn't fix why it filled |
| "Inject it and it'll settle" | Long-term follow-up of corticosteroid injection for traumatic olecranon bursitis exists [9]. Ask yourself why that study was needed |
| The swelling is the problem | The swelling is the symptom. The elbow that keeps meeting a surface is the problem |
First-line management, for a reason: activity modification and protective padding.
2 · SE — THE SUBJECTIVE PATTERN (the 70%)
Main problem
"There's a lump on my elbow." Localised swelling over posterior elbow.
Note what they didn't say. Mild ache or pressure pain, usually non-severe. A patient whose main problem is pain rather than the lump is a different conversation — go to section 4.
Body chart
Directly over the olecranon, posterior, well demarcated. Local, and it should stay local. Erythema that extends beyond the swelling is section 4.
Behaviour
Eased by rest and compression. Full but painful end-range flexion (OE line, and it belongs here too — flexion stretches the skin over a distended bursa).
Aggs: leaning on it, full bend, anything pressing on the point of the elbow — a desk edge, a car armrest, a floor, a bench.
Eases: taking the pressure off, compression.
Severity: VAS 0–10 at best / at worst / right now.
Ask specifically what their elbows rest on for hours a day. Desk, car door, armchair, wheelchair, workbench, floor (plumbers, tilers, mechanics, gardeners, students studying). The answer to that question is the treatment.
History
May follow trauma, repetitive leaning, or friction. Three mechanisms, and the third is the one people don't report because friction doesn't feel like an injury.
Ask whether this has happened before. Clinical pearl: recurrent bursitis suggests occupational or mechanical cause. A recurrence is a history-taking failure waiting to be corrected, not a treatment failure.
Special / screening questions
- Any fever, chills, or feeling generally unwell? Every time. Section 4.
- Any break in the skin — a graze, a scratch, a crack, a shaving nick? Possible redness or warmth (rule out infection).
- Gout, pseudogout, rheumatoid arthritis? Pearl from the septic page: always check for trauma + infection + rheumatologic history. The olecranon bursa is a classic site for both gout and rheumatoid nodules, and neither responds to padding.
- Diabetes, immunosuppression, steroids, dialysis?
- Occupation and hobbies, in detail.
Assessing this region? Download the Elbow assessment template →
3 · HYPOTHESIS RANKING
| Pattern | The one discriminating feature |
|---|---|
| Aseptic olecranon bursitis | A localised, fluctuant swelling that hurts far less than it looks, with no warmth, no erythema beyond the bursa, and no systemic symptoms. |
| Septic olecranon bursitis | Warmth, erythema, disproportionate pain, and systemic symptoms — with a skin break in the story. Read further: characteristics and management [10], French recommendations [11]. Its own page, free forever. |
| Gout or pseudogout | Sudden, exquisitely painful, hot and red, often with a previous attack elsewhere. The olecranon bursa is a classic site. Clinically hard to separate from sepsis — which is why the answer is the same: refer. |
| Rheumatoid nodule | Firm rather than fluctuant, often multiple, often bilateral, in someone with known or suspected RA. Doesn't respond to padding. |
| Olecranon fracture | A fall onto the point, focal bony tenderness, and an extension deficit. Its own page. |
| Triceps tendon rupture | Posterior swelling with a palpable gap and weak or absent resisted elbow extension. Read further: triceps tendon rupture from anatomy to surgical treatment [12]. Rare, missable, and surgical. |
The discriminator that does most of the work: is it warm, and can they extend against resistance.
4 · RED FLAGS — DON'T MISS THIS
Free forever. Never gated.
The first pearl is the red flag.
1. Infection — the first pearl
Clinical pearl: rule out infection — look for warmth and systemic symptoms.
Erythema or warmth if septic — medical referral. Antibiotics if septic bursitis suspected.
Escalate the same day if any of these are present:
- Fever, rigors, or feeling systemically unwell.
- Warmth, compared with the other elbow using the back of your hand.
- Erythema extending beyond the bursa, especially a margin that has moved.
- Pain out of proportion to the swelling — this presentation is normally less painful than it looks, so "it really hurts" is a change of category.
- Any break in the skin in the story, however small.
- Immunosuppression, diabetes, long-term steroids, or dialysis.
Do what the septic page says: draw the margin, write the time on it, record a temperature, and refer today rather than review next week. The septic page is free forever — send them there.
The trap: a clear mechanical cause does not exclude infection. The graze from the fall, or the friction that broke the skin over weeks of kneeling, is often how it got in.
2. Triceps tendon rupture
Posterior elbow swelling with a palpable gap above the olecranon and weak or absent resisted extension is not bursitis. Read further: triceps tendon rupture from anatomy to surgical treatment (Celli et al. 2015). Test resisted elbow extension on every posterior elbow swelling. It takes five seconds and it is the one thing that would be catastrophic to miss here.
3. A chronic bursa that has changed character
A long-standing, thickened bursa that develops new pain, ulceration, a non-healing wound, or a change in the overlying skin needs a medical opinion rather than more padding. Chronic olecranon bursitis has been reported as a risk factor for squamous cell carcinoma in a case report [13]. A single case report is not a probability — it is a reason not to keep padding skin that isn't healing.
4. Crystal or inflammatory disease behind it
Sudden, hot, exquisitely painful, or recurrent in someone with gout, pseudogout or rheumatoid arthritis — that is a medical problem with a medical treatment, and padding won't touch it. Refer, and say what you suspect.
5 · OE — THE OBJECTIVE (the 30%)
Members
Sections 5 to 7 are for members
The objective exam, management and pearls, plus the six-minute lesson and the debrief. Free with an account.
Sign in or join free6 · MX — MANAGEMENT ESSENTIALS
Members
Sections 5 to 7 are for members
The objective exam, management and pearls, plus the six-minute lesson and the debrief. Free with an account.
Sign in or join free7 · CLINICAL PEARLS + RETRIEVAL CHECK
Members
Sections 5 to 7 are for members
The objective exam, management and pearls, plus the six-minute lesson and the debrief. Free with an account.
Sign in or join freeMembers
The 5-minute lesson is for members
Twelve slides on this pattern: what you'll hear, what to examine, what to do. Free with an account.
Sign in or join freeGuideline anchor
No Australian guideline, and no clinical practice guideline for the aseptic condition.
More
The management anchor is a systematic review of non-surgical treatment of aseptic olecranon bursitis (Kaur et al. 2023, PMID 37945181), with treatment systematically reviewed earlier (Sayegh et al. 2014, PMID 25234151) and clinical management reviewed in the Journal of Hand Surgery (Nchinda et al. 2021, PMID 33840568). The single most useful study is a randomised trial in Clinical Orthopaedics and Related Research comparing compression plus NSAIDs against other approaches (Kim et al. 2016, PMID 26463567), published with a CORR Insights commentary (Kennedy et al. 2016, PMID 26493988). For the condition this page exists to exclude, the 2023 French recommendations on prepatellar and olecranon septic bursitis apply (Darrieutort-Laffite et al. 2024, PMID 37995861).
None of these is a clinical practice guideline for aseptic bursitis, because none exists. The French recommendations govern the septic condition — the thing this page exists to exclude — and are medical, not physiotherapy, documents.
Members
The evidence summary is for members
Verified diagnostic accuracy, where the evidence stands and what it doesn't settle. Free with an account.
Sign in or join freeSources · 20
ShowHide
Every source on this page resolves and title-verifies against PubMed. Newest first.
- 2024Shemesh et al. (2024). Risk Factors for the Development of Olecranon Bursitis-A Large-Scale Population-Based Study. Journal of clinical medicine, 13(24). https://doi.org/10.3390/jcm13247801
- 2022Subramanian et al. (2022). Olecranon Bursitis Secondary to Trauma. Cureus, 14(7), e27306. https://doi.org/10.7759/cureus.27306
- 2017Raas et al. (2017). Treatment and outcome with traumatic lesions of the olecranon and prepatellar bursa: a literature review apropos a retrospective analysis including 552 cases. Archives of orthopaedic and trauma surgery, 137(6), 823-827. https://doi.org/10.1007/s00402-017-2690-2
- 2017Khodaee (2017). Common Superficial Bursitis. American family physician, 95(4), 224-231. PubMed 28290630
- 2016Kim et al. (2016). A Randomized Trial Among Compression Plus Nonsteroidal Antiinflammatory Drugs, Aspiration, and Aspiration With Steroid Injection for Nonseptic Olecranon Bursitis. Clinical orthopaedics and related research, 474(3), 776-83. https://doi.org/10.1007/s11999-015-4579-0
- 2016Kennedy (2016). CORR Insights(®): A Randomized Trial Among Compression Plus Nonsteroidal Antiinflammatory Drugs, Aspiration, and Aspiration With Steroid Injection for Nonseptic Olecranon Bursitis. Clinical orthopaedics and related research, 474(3), 784-6. https://doi.org/10.1007/s11999-015-4608-z
- 2023Kaur et al. (2023). Non-surgical treatment of aseptic olecranon bursitis: A systematic review. Reumatologia clinica, 19(9), 482-487. https://doi.org/10.1016/j.reumae.2023.05.004
- 2014Sayegh & Strauch (2014). Treatment of olecranon bursitis: a systematic review. Archives of orthopaedic and trauma surgery, 134(11), 1517-36. https://doi.org/10.1007/s00402-014-2088-3
- 1984Weinstein et al. (1984). Long-term follow-up of corticosteroid injection for traumatic olecranon bursitis. Annals of the rheumatic diseases, 43(1), 44-6. https://doi.org/10.1136/ard.43.1.44
- 2023Nguyen et al. (2023). Characteristics and management of olecranon or prepatellar septic bursitis. Infectious diseases now, 53(2), 104652. https://doi.org/10.1016/j.idnow.2023.104652
- 2024Darrieutort-Laffite et al. (2024). 2023 French recommendations for diagnosing and managing prepatellar and olecranon septic bursitis. Joint bone spine, 91(2), 105664. https://doi.org/10.1016/j.jbspin.2023.105664
- 2015Celli (2015). Triceps tendon rupture: the knowledge acquired from the anatomy to the surgical repair. Musculoskeletal surgery, 99 Suppl 1, S57-66. https://doi.org/10.1007/s12306-015-0359-y
- 2026Holt et al. (2026). Case Report: Chronic Olecranon Bursitis as a Risk Factor for Squamous Cell Carcinoma. Journal of orthopaedic case reports, 16(3), 149-153. https://doi.org/10.13107/jocr.2026.v16.i03.6922
- 2022Beyde et al. (2022). Efficacy of empiric antibiotic management of septic olecranon bursitis without bursal aspiration in emergency department patients. Academic emergency medicine : official journal of the Society for Academic Emergency Medicine, 29(1), 6-14. https://doi.org/10.1111/acem.14406
- 2019Wu et al. (2019). Clinical efficacy of ultrasound-guided injection in the treatment of olecranon subcutaneous bursitis. Journal of X-ray science and technology, 27(6), 1145-1153. https://doi.org/10.3233/XST-190562
- 2024McDermott et al. (2024). Intrabursal Doxycycline Sclerotherapy for Recurrent Olecranon Bursitis of the Elbow: A Case Control Study. Journal of hand surgery global online, 6(4), 504-509. https://doi.org/10.1016/j.jhsg.2024.03.006
- 2024Simpson et al. (2024). No Wound Healing Complications or Recurrences Were Seen and a High Level of Satisfaction Was Reported in Patients Who Underwent Endoscopic Olecranon Bursectomy for Recalcitrant Olecranon Bursitis. Arthroscopy, sports medicine, and rehabilitation, 6(1), 100832. https://doi.org/10.1016/j.asmr.2023.100832
- 2024Shen et al. (2024). Clinical efficacy of endoscopic debridement combined with compression suture in the treatment of recalcitrant aseptic olecranon bursitis. Journal of orthopaedic surgery and research, 19(1), 596. https://doi.org/10.1186/s13018-024-05090-3
- 2013Tu et al. (2013). Olecranon extrabursal endoscopic bursectomy. Techniques in hand & upper extremity surgery, 17(3), 173-5. https://doi.org/10.1097/BTH.0b013e31829c0535
- 2021Nchinda & Wolf (2021). Clinical Management of Olecranon Bursitis: A Review. The Journal of hand surgery, 46(6), 501-506. https://doi.org/10.1016/j.jhsa.2021.02.006
Mapped to this pattern
Generic measures that also apply
- Borg RPE
Borg Rating of Perceived Exertion Scale (6-20)
perceived exertion · 1 items · 1 min
- DASH
Disabilities of the Arm, Shoulder and Hand
upper limb disability · 30 items · 8 min
- GROC
Global Rating of Change Scale
perceived change since baseline · 1 items · 1 min
- NPRS
Numeric Pain Rating Scale
pain intensity · 1 items · 1 min
- PGIC
Patient Global Impression of Change
perceived change since baseline · 1 items · 1 min
- PSFS
Patient-Specific Functional Scale
patient-generated function · 3 items · 2 min
- QuickDASH
QuickDASH
upper limb disability, short form · 11 items · 4 min
- SANE
Single Assessment Numeric Evaluation
patient-rated function as a percentage of normal · 1 items · 1 min
- UEFI
Upper Extremity Functional Index
upper limb function · 20 items · 5 min
- VAS
Visual Analogue Scale
pain intensity · 1 items · 1 min
- Borg CR10
Borg Category Ratio 10 Scale
perceived exertion or symptom intensity, ratio scale · 1 items · 1 min
- GAS
Goal Attainment Scaling
individualised goal achievement · 10 min
Did this page do its job?
CliniStudy is in beta. One tap is enough — it decides what gets fixed first.